Pragmatische directe benaderingen voor tandslijtage van GC
👆 Klik op een van de onderstaande stappen voor meer informatie.
 Identificatie
 Strategie
- Pre-restoratieve orthodonte
- Dahl-principe
- Volledige gebitsrehabilitatie
Directe technieken
EN / OF
Indirecte workflow
 Onderhoud
ondervindt slaapbruxisme *
*Azeez, A. A., Sheri f, S., & Franca, R. (2021). Statistical estimation of wear in permanent teeth: a systematic review. Dentistry Review, 1(1), 100001.
ondervindt tandslijtage**
**Zieliński, G., Pająk, A., & Wojcicki, M. (2024). Global prevalence of sleep bruxism and awake bruxism in pediatric and adult populations: a systematic review and meta-analysis. Journal of Clinical Medicine, 13(14), 4259.
Identificatie
Gebitsslijtage is meestal multifactorieel en een combinatie van de volgende vier soorten slijtage.
Erosion

Typische gladde oppervlakken veroorzaakt door zuren in voedsel, dranken en/of maagzuren
– Met dank aan Dr. P. Swerts, België
Abrasie
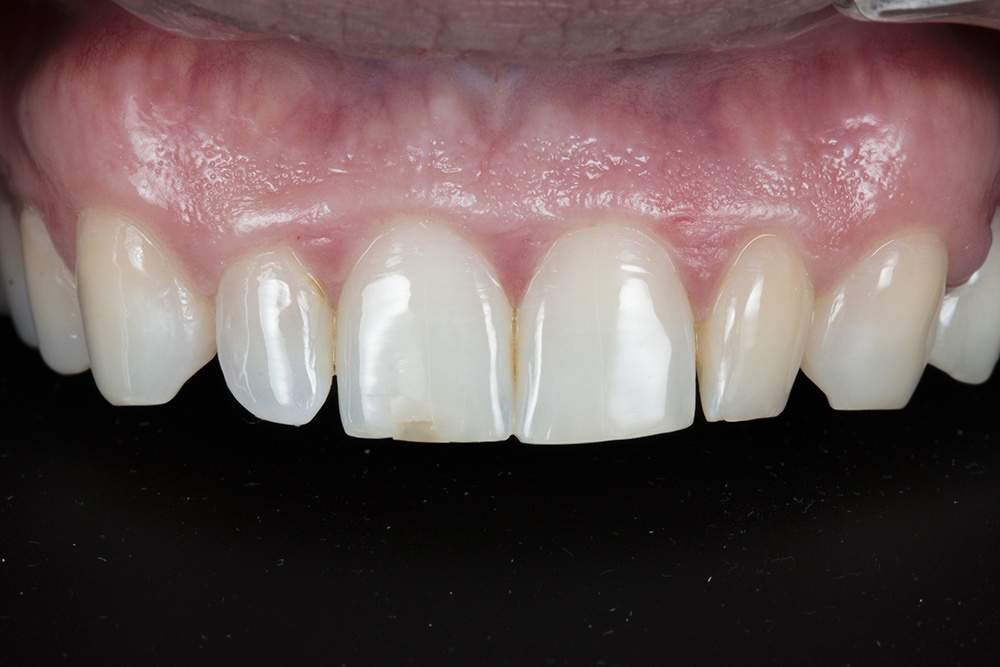
U-vormige inkepingen cervicaal of andere atypische slijtageletsels door vreemde voorwerpen of gewoontes
– Met dank aan Dr. A. Salehi, Frankrijk
Attritie
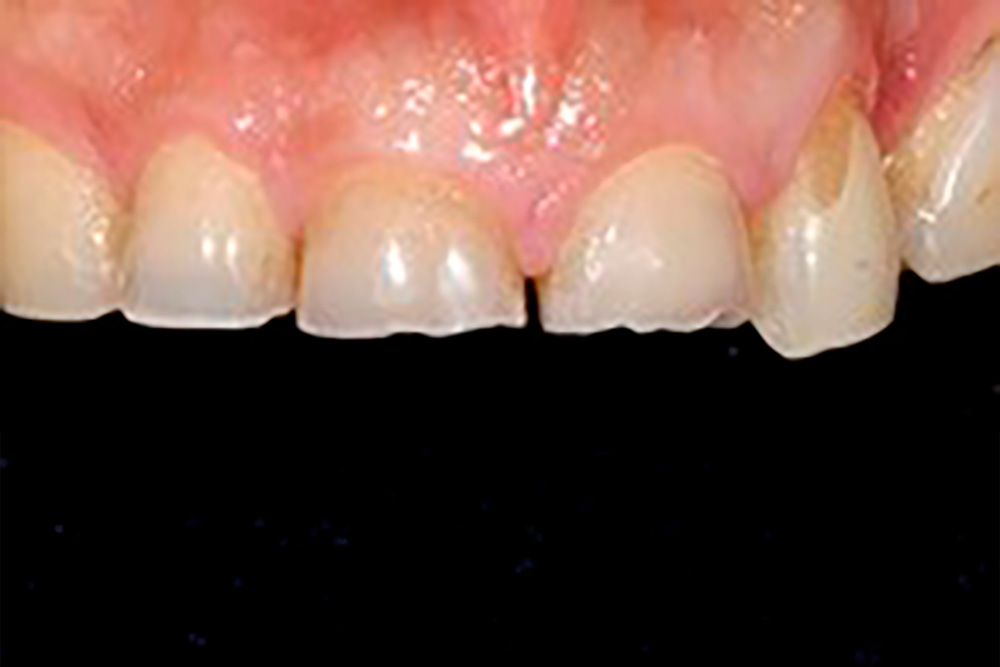
Afgeplatte oppervlakken, door tand-op-tand-contact bij schuren, klemmen en kauwen
– Met dank aan Dr. K. Karagiannopoulos, VK
Abfractie

Cervicale caviteiten door herhaalde flexie klemmen en knarsen
– Met dank aan Dr. S. Moretto, Brazilië
Strategieën
Een pre-restauratieve orthodontische behandeling is nodig wanneer de patiënt een malocclusie heeft en slijtage aanwezig is in de anterieure of posterieure regio. Wanneer de slijtage enkel de anterieure dentitie betreft, kan het Dahl-principe worden gebruikt in plaats van een orthodontische behandeling. Tot slot, als er sprake is van veralgemeende slijtage maar de occlusie normaal is en de tanden goed uitgelijnd zijn, dan is enkel restauratief herstel voldoende.
Pre-restauratieve orthodontie

gevolgd door volledige gebitsrestauratie
Meest geschikt voor: gevallen van dento-alveolaire compensatie of wanneer malocclusie of crowding aanwezig is.
– Met dank aan Dr. S. Daroste, Zweden
Dahl-Principle

Meest geschikt voor: Patiënten met gelokaliseerde slijtage in het front. Door herstel van het front (hier een witte wax-up) in supraocclusie, kan er posterieur een relatieve axiale verschuiving ontstaan, waardoor de uiteindelijke occlusie kan worden bereikt.
– Met dank aan Dr. K. Karagiannopoulos, Verenigd Koninkrijk
Enkel volledige gebitsrestauratie

Meest geschikt voor: Algemene tandslijtage zonder malocclusie
– Met dank aan prof. M. Peumans, België

TIP! Occlusale verticale dimensie (OVD)
De nieuwe OVD wordt eerst bepaald door de benodigde lengte die aan de voorste tanden moet worden toegevoegd. Wijzigingen aan OVD variëren doorgaans van 2 tot 5 mm, afhankelijk van de tolerantie van de patiënt en de vereiste minimale dikte van het restauratieve materiaal. De freeway space moet behouden blijven. Hulpmiddelen zoals diagnostische wax-ups, digital smile design en articulatoren, zowel conventioneel als digitaal, helpen bij het veilig en voorspelbaar aanpasseng voor functionele en esthetische rehabilitatie.

Gebruik REVOTEK LC van GC voor het deprogrammeren
- Makkelijk te vormen
- Bepaal het moment van uitharden (met licht)
- Occlusie kan meerdere keren gecheckt worden zonder vervormingen
TIP!
- Houd het model tijdens de procedure in de buurt, vooral bij het restaureren uit vrije hand, zodat je je voortgang regelmatig kan controleren.
- Vermijd te lange of vermoeiende afspraken. Plan pauzes indien nodig en overweeg de behandeling over meerdere dagen te verdelen.
Technieken/workflow
Directe restauraties
Voorbereiding van tanden vóór behandeling:
- Controleer de toestand van het tandvlees en reinig alle tanden.
- Goede isolatie voorkomt problemen zoals microlekkage, loslating en postoperatieve gevoeligheid.
- Voor een groter retentiegebied en een betere esthetische gradiënt wordt aangeraden om een glazuurbevel te creëren.
TIP!
Rond eventuele tandbleekbehandelingen minimaal twee weken vóór de restauratieve behandeling af voor een optimaal resultaat.


Opbouw uit vrije hand
Het beste geschikt wanneer: De patiënt eenvoudige behandelbehoeften heeft waarbij een beperkt oppervlak is aangedaan. Het gebruik van G-ænial A’CHORD biedt uitstekende handling, esthetiek en weerstand tegen slijtage.
Benodigde tools: model met eindontwerp en siliconensleutel


Met dank aan Dr. R. Zunzarren, Frankrijk

Malperstechniek (MPT)
Het meest geschikt wanneer: De patiënt een matig complexe behandelbehoefte heeft waarbij meerdere tanden zijn aangedaan door slijtage. Deze techniek lijkt op de injectietechniek, maar gebruikt pastacomposiet om op te bouwen. Het gebruik van G-ænial A’CHORD met de malperstechniek geeft de restauratie een prachtige glans die houdt.
Benodigde hulpmiddelen: model met alternerend opbouwde tanden; model met alle tanden opgebouwd; rigide transparante siliconensleutel of, als alternatief: rigide siliconensleutel gerebased met EXACLEAR

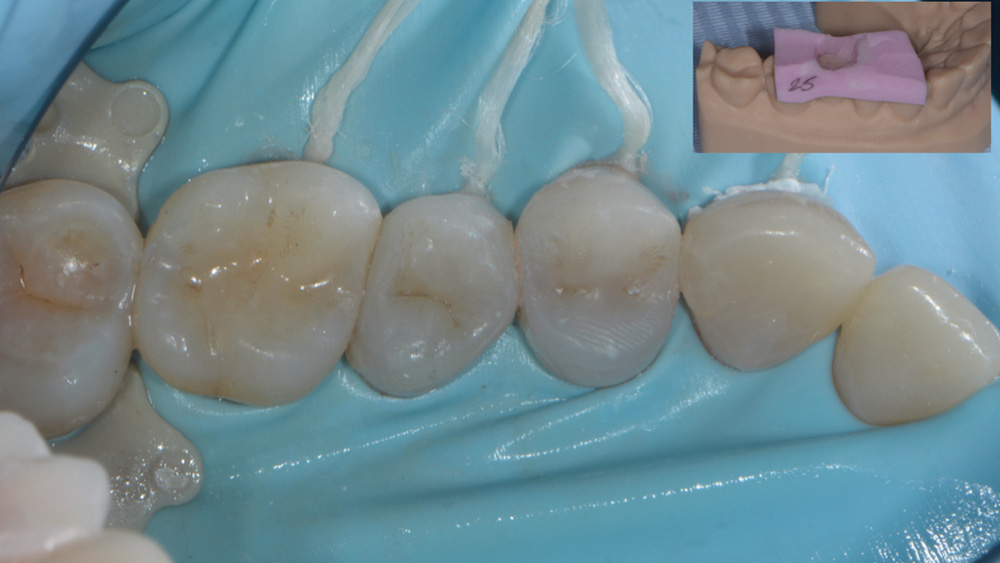


Met dank aan prof. M. Peumans, België

Injectietechniek (MIT)
Het beste geschikt wanneer: De patiënt een complexere behandelbehoefte heeft waarbij meerdere tanden zijn aangedaan door slijtage. Deze techniek is uitstekend om een gedetailleerd design snel en voorspelbaar naar de mond over te brengen. Het gebruik van G-ænial Universal Injectable, ons sterkste restauratief composiet met ideale thixotropie, heeft de voorkeur voor de beste resultaten.
Benodigde hulpmiddelen: model met alternerend opgebouwde tanden; model met alle tanden opgebouwd; transparante siliconensleutel

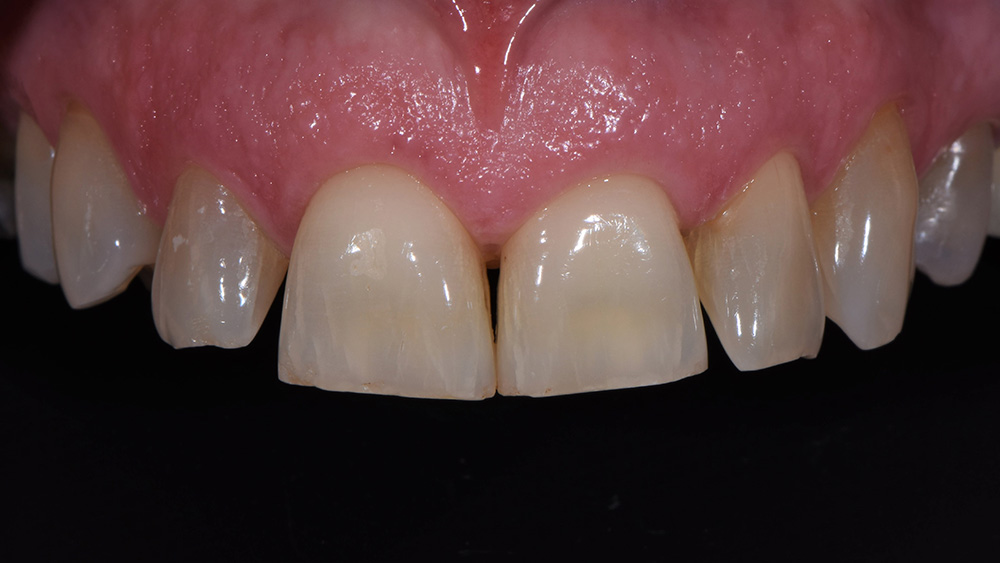


Met dank aan Dr. M. Fostiropoulou, Griekenland
TIP!
Wenst u extra bescherming tegen breuken? Breng everX Flow aan als dentinevervanger voordat je de restauratie voltooit met één van de drie voorgestelde technieken.

Materiaalselectie

- Quick bonding procedure and cost-efficient dispensing with 300 drops per bottle
- Ideal to block hypersensitivity caused by wear

- Long-lasting gloss, preserving your aesthetics even longer for your freehand or stamp technique
- The true-to-nature fluorescence ensures that your wear solution is invisible under any light

- Superior wear resistance, making it an ideal composite to treat wear with
- Self-polishing ability for long term gloss and reduced wear of antagonist

- Strengthening teeth in case of heavy occlusal loading
- Very high fracture resistance to inhibit shock effects caused by bruxism
Indirect restorations

Clear communication between clinician and laboratory is key to achieving a functional and aesthetic rehabilitation.
Intermediate phase
When treating severe tooth wear, an important step is the transitional phase, during which the new VDO, is tested before starting definitive treatments.
Key parameters to evaluate during the transitional phase:

Absence of pain

Function (e.g. occlusion)

Aesthetics

Speech

Adaptation/comfort with new VDO

Conventional temporisation

Material selection
| PMMA | Composite Resin (e.g. bis- acryl material, direct composite, ...) | |
|---|---|---|
| Features |
|
|

3D printable light-curing composite for temporary crowns & bridges
- Excellent stable mechanical properties
- MMA-free/for DLP printing
- Compatible with OPTIGLAZE color
More information

Dual-cure bisacrylic composite for temporary crowns & bridges
- Non-sticky handling
- High fracture toughness
- Quick polish, lasting gloss
- Repairable and rebaseable
Final restoration
The choice of the restoration in tooth wear cases should follow a minimally invasive principle, trying to preserve as much healthy tooth structure as possible. The selection of the kind of the restoration depends on how much tooth structure is lost and on the remaining tooth integrity.
Veneer

Rounded internal angles
Keep minimum thickness accordingly to manufacturer’s instructions
If possible, the restoration should be located in the enamel
Sharp finishing line on the enamel to avoid chipping of the restoration
- Minor to moderate tooth structure loss with enamel support
- Minimal functional loading on veneers
- Wear mainly confined to enamel or superficial dentin; moderate loss of tooth length
More info on veneer preparation
Overlay

6°-10° axial wall taper
Keep minimum thickness accordingly to manufacturer’s instructions
Smooth finish line
Rounded intersection corner
- Moderate to severe tooth structure loss involving cuspal structure
- Partial preservation of axial walls
- Occlusal instability
More info on indirect partial restorations
Crown

6°-10° axial wall taper
Keep minimum thickness accordingly to manufacturer’s instructions
Smooth finish line
Rounded intersection corner
- Weakened structure, severe wear or damage
- Extensive dentin exposure with minimal or no enamel support
- High incisal/occlusal load when veneers or overlays are insufficient
Discover the entire crown workflow
Material selection

Initial LiSi Block & Press
Lithium disilicate solutions for milling and pressing
- High wear resistance
- Strong, easy milling
- Smooth, low-roughness surface
- HDM technology
- Beautiful aesthetics
More information for dental techniciansMore info for dentists

CERASMART270
Force absorbing hybrid ceramic CAD/CAM block
- Homogeneous filler dispersion – strong, smooth and long-lasting
- Buffers heavy bit forces
- Easy chairside repair
- Compatible with OPTIGLAZE color

Initial zirconia solutions
High-strength zirconia disks and characterisation options
- Omni-functional: broad range of indications, regular or fast sintering
- Thin restorations for vertiprep possible
- Available in ST, HT, UHT or Multilayer
Discover our Zr solutions

|

|

|
||
|---|---|---|---|---|
| Category | Lithium disilicate | Hybrid ceramic | Zirconia | |
| Materials | Initial LiSi Block | CERASMART270 | Initial Zirconia Disk & Initial Zirconia Disk ML Elite |
|
| Physical properties |
Biaxial Flexural Strength (MPa) |
408 | 270 | 600-1200 |
| Elasticity/Buffering masticatory forces |
- | +++ | - | |
| Preventing antagonist wear | + | +++ | + | |
| Handling | Intra-oral repair | + | +++ | + |
| Polishability | +++ | +++ | + | |
| Fast Processing | ++ | +++ | + | |
| Aesthetics | Aesthetics | +++ | ++ | ++ |
| Anterior indications | +++ | + | + | |
| Characterisation options | IQ ONE SQIN Initial LiSi |
OPTIGLAZE color/ GRADIA PLUS Lustre Paint |
Initial Zr-FS / Initial IQ ONE SQIN |
Finishing

Polishing of Initial LiSi Block restoration

Remove sprue with a diamond disc.

Polish with coarse polishing disc.

Polish with medium polishing disc.

Finish with fine polishing disc.

Polish with goat hair wheel and GRADIA DIAPOLISHER paste (optional).

Final result.
Painting of Initial LiSi Block restoration
Remove sprue with a diamond disc.

Set the base by glazing with L-NFL shade of Initial IQ Lustre Pastes ONE.


Paint with L-A shade of Initial IQ Lustre Pastes ONE for dentin effects.

Fire.
Detailed firing instructions can be found in the Initial Lustre Pastes ONE Technical Manual.

Final result.

Polishing of CERASMART270 restoration

Remove sprue with a diamond disc.

Polish with medium polishing disc.

Polish with fine polishing disc.

Polish with goat hair wheel and GRADIA DIAPOLISHER paste (optional).

Final result.
Painting of CERASMART270 restoration

Remove sprue with a diamond disc.

Paint the fissures and cervical areas with OPTIGLAZE color.

Add gloss with OPTIGLAZE color Clear HV.

Light-cure according to the manufacturer’s instructions.

Final result.
Polishing of Zirconia restoration


Use only dedicated dental instruments for preparation & finishing of zirconium, lithium disilicate & veneering ceramics.


Individual adjustment of gloss level can be done using dedicated instruments and diamond paste.
Courtesy of MDT C. Fischer, Germany
Painting of Zirconia restoration


The framework is shaped and contoured using dedicated instruments. After pre-polishing with a dedicated ceramic polisher, the finished framework as well as the surfaces, which require ceramic application, are softly sandblasted with 50 microns Alu-Oxid at max. 1,5 bar pressure.


After the final firing, an unsurpassed vitality and a very natural glaze is easily obtained.
The convincing natural end-result is achieved in just one Lustre Pastes ONE firing!
Courtesy of MDT M. Brüsch, Germany
Luting

Lithium disilicate
Etch with 5-9% HF for 20 sec.

Hybrid ceramics
Etch with 5-9% HF for 60 sec OR
Sandblast (30–50 μm Al2O3, ~1 bar).

Zirconia
Sandblast (25- 50 μm Al2O3, 1–2 bar).
Restoration primer with silane is required for glass ceramics and hybrid ceramics;
Restoration primer with MDP is optional for zirconia with G-CEM ONE.
G-Multi PRIMER can be used for any restoration.
Restoration primer with MDP is optional for zirconia with G-CEM ONE.
G-Multi PRIMER can be used for any restoration.
G-CEM ONE
Universal resin cement

- Universal and self-adhesive
- High bond strength in all modes
- Resistant to discolouration
- High wear resistance
Tooth primer is recommended for preparations that lack retention and resistance shape.
G-CEM ONE Adhesive Enhancing Primer (or G-Premio BOND + light-cure) can be used for any occasion.
G-CEM ONE Adhesive Enhancing Primer (or G-Premio BOND + light-cure) can be used for any occasion.


No restoration primer
required with FujiCEM Evolve
required with FujiCEM Evolve
FujiCEM Evolve
Resin modified glass ionomer cement

- Moisture-tolerant & low water absorption
- Fast workflow
- Easy clean-up
- Excellent for zirconia
No tooth primer required
with FujiCEM Evolve
with FujiCEM Evolve
Prepare the teeth for the treatment

Check gingival health and clean all the teeth.
Courtesy of Prof. M. Peumans, Belgium

Clean the surface with pumice and water.


Sandblasting the surface is recommended to ensure a clean working area.
Courtesy of Dr. P. Swerts, Belgium
Cases

Extraoral front view before treatment. The shortened and flattened upper anterior crowns significantly affected the patient’s smile aesthetics and contributed to a notable psychological burden.

Intraoral view before treatment: incisal grooving and occlusal cupping indicate a strong erosive component. Note that the right side is more affected than the left side, which might indicate an habitual asymmetric occlusal loading. Amalgam restorations appear shiny and untarnished, which might indicate an acidic environment.

Intraoral buccal view before treatment. Wide and flattened erosive areas can be seen on the buccal surfaces.

Facially driven workflow: Intraoral mock-up to test the length of the anterior teeth

A bilaminar technique using G-ænial A’CHORD (GC) and
G-ænial Universal Injectable (GC) as the final layer was employed for the anterior restorations. All adhesive procedures were carried out under rubber dam.

Semi-indirectly prepared injection moulding restorations reduce chair time while making finishing easier.
a: G-ænial Universal Injectable restorations on a printed model.
b: teeth were isolated and gently sandblasted prior to luting.

Occlusal view of the lower arch. The Initial LiSi Press restorations were not veneered, resulting in an exceptionally smooth, highly polished surface that maintains excellent aesthetics.

Intraoral buccal view after treatment.

A natural surface morphology and texture were restored after treatment.

Extraoral frontal view after treatment. The natural youthful tooth length and curvature were restored, with the upper incisors gently following the contour of the lower lip and an increased exposure of the teeth during smiling.
Courtesy of Dr Zohaib Al, UK
Prevention and maintenance
A holistic approach is paramount when dealing with wear. It is necessary to assess its underlying risk factors (e.g. disease, eating habits,…) prior to establishing any treatment strategy. A regular surveillance of the wear progression is needed before intervention, especially at early stages of wear. Using a tooth wear index, pictures, or 3D scans can help to analyse wear progression over time. Finally, the patient must be aware of any wear-inducing habits and must comply with preventing further damage to the tooth tissue or eventual restorations for a successful outcome.
Night Guards
Prevent further wear by recommending a night guard when clinically indicated

Oral Hygiene
Ensure your patient brushes frequently, but not too aggressively, and with the right tools

Attitude
Change patients’ perspective on how to treat and protect their teeth and restorations

Diet
Limit acidic beverages and food, such as energy drinks and citrus fruits, which accelerate wear
In office maintenance

MI Varnish, Tooth Mousse and MI Paste Plus contain RECALDENT™ CPP-ACP which:
- Promotes the remineralisation of enamel and an increase in surface hardness. When the surfaces are remineralising faster and become stronger, wear can be inhibited.
- Desensitises teeth with exposed dentin
- Provides extra protection against future acid attacks
RECALDENT™ and RECALDENT™ logo are trademarks of Mondelēz International Group used under license.
RECALDENT™ is derived from milk casein. Do not use on patients with a milk protein, hydroxybenzoates or soy bean allergy.

At home maintenance

FAQ
How often do you recall and reassess wear progression post-treatment?
Recalls post-treatment are often indicated by your scoring-/evaluation system of choice by severity and risk. This could mean that for stable wear, yearly visits could be sufficient, while it could be preferred to see your high-risk patients in a timespan of less than 6 months.
Are night guards useful or not?
Night guards act as a physical barrier to protect teeth from attritional forces. They are strongly recommended for patients with nightly bruxism. However, for patients with erosion or malocclusion, their use may be counterproductive.
When should pre-restorative orthodontics be considered in treating wear?
Patients with tooth wear often present with misaligned teeth, as progressive wear reduces tooth size over time. Hence, orthodontic treatment nearly always offers significant benefits in these cases. However, it’s natural for patients to have concerns or feel hesitant before starting treatment. A great way to figure out if restorative results can be achieved without orthodontics is to carry out an additive mockup. This also serves as the patient’s consent and provides documented evidence to proceed with orthodontics.
What is the best treatment for patients with moderate wear lesions?
There is no single answer to what treatment should be used at all times. There is a great variety of dental material to choose from and techniques that can be implemented. A scoring-/evaluation system might help to understand the severity of the case and guide possible treatment options. However, the final choice generally depends on the patient’s wishes, financial resources and healthcare coverage, invasiveness of treatment, aesthetics and perceived longevity.
Do I need a deprogrammer when dealing with moderate wear?
Yes, in case you are changing the occlusal vertical dimension. It offers a reproducible occlusal position throughout all the treatment stages.
What are some key considerations to have in mind when establishing a new OVD?
The primary objective is a stable, comfortable, and functional occlusion. A mechanically perfect occlusion is not always necessary to achieve a comfortable and successful result. The new OVD is generally determined by the amount added to the anterior teeth. Changes to OVD typically range from 2 to 5 mm.


When treating wear in cases with large cavities, should I be concerned about the polymerisation shrinkage stress?
When treating wear most surfaces are flat, so the C-factor is low. This means that the shrinkage stress is quite low. It is always advised to use a composite designed with the latest technology, which will have low polymerization shrinkage and high conversion rate such as materials like G-ænial Universal Injectable and G-ænial A’CHORD.
How long do treatments with composite last for wear cases?
Research shows that patients treated for severe tooth wear in full mouth restoration have a low failure rate of 2.3% over the span of 5.5 years. Direct resin composite can offer an acceptable medium-term option for the treatment of severe, generalised tooth wear; molar restorations may require higher maintenance.
How to ensure adequate bond strength on worn, sclerotic, or eroded enamel/dentin?
Preparation of the surface is key to ensure adequate bonding strength. Roughen your surface with a bur for increased retention and achieve a clean working area by sandblasting and by making use of rubber dam. Make use of a trusted, well documented bonding system like G-Premio BOND and bond as much as possible to (healthy) enamel.
Why are MI Paste Plus and Tooth Mousse good for wear cases?
Recaldent™ (CPP-ACP) promotes the remineralisation of enamel, desensitises, lowers sensitivity and provides extra protection against acidic attacks, and therefore ideal to counteract erosion. Both MI Paste Plus and Tooth Mousse are easy to apply, well accepted, and can be used at home by the patient.
Downloads

Direct restorations
Indirect restorations
Articles